

A minimally invasive treatment for carotid artery disease that works by briefly reversing blood flow during the procedure, keeping any dislodged plaque away from the brain.
Carotid artery disease
The carotid arteries run up each side of your neck, carrying oxygen-rich blood to the brain. Damage to the arterial walls, caused either by high blood pressure, high blood sugar, smoking, high cholesterol rates, result in inflammation and ultimately, in fatty deposits called plaques, which build up inside these arteries and narrow them. This condition is called carotid artery stenosis. As that narrowing progresses, the risk that a fragment of plaque will break off and travel to the brain, causing an ischaemic stroke, grows.
In India, stroke is the fourth leading cause of death and fifth leading cause of disability. Hypertension, diabetes, and smoking, which are all prevalent in India, are among the primary risk factors for carotid disease.
When carotid artery stenosis is significant, treatment is needed to reduce stroke risk. TCAR is one option, designed specifically for patients who need effective treatment but carry higher risk from traditional open surgery.
Recognise a stroke — act immediately
- Sudden weakness or numbness in the face, arm, or leg especially on one side
- Sudden slurring of speech or difficulty understanding
- Sudden loss of vision in one or both eyes
- Sudden severe headache with no known cause
- Sudden dizziness or loss of balance
- Sudden confusion or difficulty swallowing
If any of these occur, call emergency services immediately. Time is brain tissue.
What is TCAR?
Transcarotid Artery Revascularization is a minimally invasive procedure that opens a narrowed carotid artery using a stent, reducing the risk of stroke. What makes TCAR distinct from conventional carotid stenting is a blood flow reversal system; during the critical moment when the stent is being positioned and expanded inside the narrowed artery, blood is temporarily redirected away from the brain, passed through an external filter, and returned through a tube in the femoral vein. When the stent is being placed, the artery wall disturbed and this is when plaque fragments are most likely to break off. Any plaque that dislodges during the contact is caught by the filter rather than reaching the brain.
The procedure is performed in a hybrid operating room, takes under an hour in most cases, and requires a small incision roughly 2–3 cm just above the collarbone rather than a long cut along the neck.
Who is a candidate for TCAR?
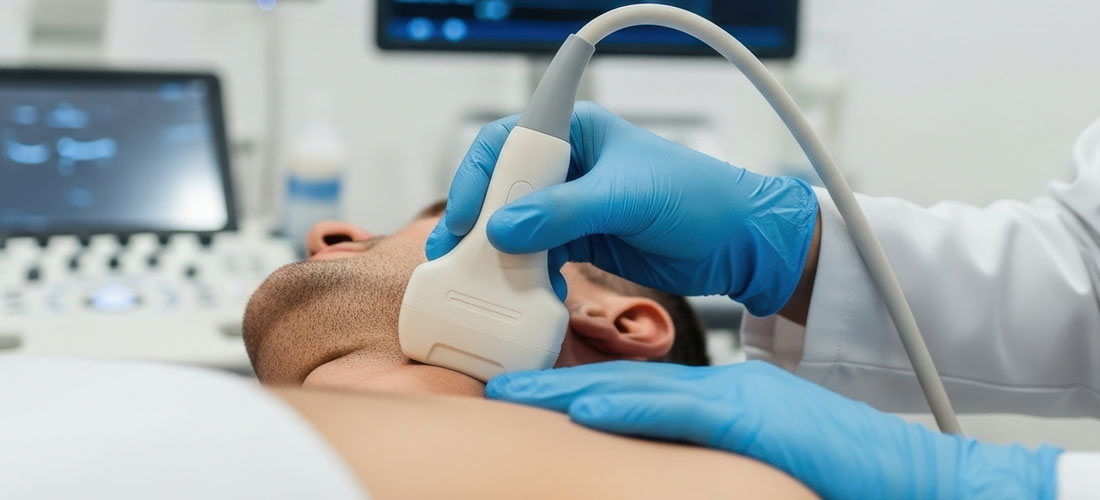
TCAR is considered for patients with confirmed carotid artery disease where the benefit of intervention outweighs the risk. Eligibility is confirmed after imaging (carotid ultrasound or CT angiography) and a full assessment of your health.
TCAR is typically recommended when:
- There is moderate to severe narrowing of the carotid artery, generally 50% or greater in patients who have had symptoms, or 70% or greater in patients without symptoms
- Open surgery carries elevated risk due to advanced age, previous neck surgery, significant cardiac or pulmonary conditions, or anatomy that makes endarterectomy more difficult
- Imaging confirms that the anatomy is suitable for direct carotid access above the collarbone
Understanding TCAR
What happens during the procedure
TCAR can be performed under local anaesthesia where you are awake but sedated and feel no pain, or under general anaesthesia. Under local anaesthesia, your surgeon can ask you simple questions throughout the procedure to monitor brain function in real time.
Step 1: Access
A small incision is made just above the collarbone to reach the common carotid artery directly.
Step 2: Flow reversal
A tube is placed into the carotid artery and connected to a flow reversal circuit. Blood flows away from the brain, passes through an external filter, and is returned via a second tube in the femoral vein at the groin. This is TCAR’s unique brain-protection mechanism.
Step 3: Stent placement
Working through the same access point and guided by real-time imaging, the surgeon delivers a stent to the narrowed segment of the artery, opening it and stabilising the plaque against the vessel wall.
Step 4: Closure
Once the stent position is confirmed, normal blood flow is restored. The incision is closed with absorbable sutures so there are no staples to remove. A dressing is applied that will come off the following day.
Recovery after TCAR
Recovery from TCAR is faster than from open carotid surgery. The smaller incision means less pain and a shorter hospital stay.
Typically one overnight hospital stay is the general rule. Monitoring continues through the night, and you will be discharged usually the following morning if there are no concerns.
We encourage light walking from day one. For the first week, avoid driving in the first 24 hours and hold off on heavy lifting, cycling, or strenuous exercise.
A blood-thinning regimen of aspirin plus clopidogrel is prescribed to prevent clot formation in the stented artery. Take these exactly as directed and do not stop without consulting your surgeon first. The duration is usually at least one month, and often longer depending on your overall cardiovascular risk.
Remove the dressing 24 hours after the procedure. Wash the site gently with soap and water and pat dry. The scar is typically small and fades well.
A carotid duplex ultrasound is scheduled at 30 days and then annually to check that the stented artery remains open and to detect any re-narrowing (restenosis) early.
Contact RIVEA or go to emergency if you notice sudden weakness, changes in speech or vision, unusual swelling or oozing at the incision site, or any sign of infection.
How TCAR compares to carotid endarterectomy (CEA)
The traditional open surgery, called carotid endarterectomy remains the most studied approach to carotid disease. For younger, healthier and low-risk patients it remains the gold standard. TCAR is an alternative option for patients in whom CEA carries elevated risk.
| TCAR | Carotid Endarterectomy (CEA) | |
|---|---|---|
| Incision | Small (2–3 cm), above collarbone | Longer incision along the side of the neck |
| Brain protection | Active blood flow reversal with external filter | Surgical technique; shunting in selected cases |
| Peri-operative stroke risk | Sub-3% across real-world registries | ~1–2% in standard-risk patients in landmark trials |
| Hospital stay | Typically 1 night | 1–2 nights on average |
| Return to activity | Most patients within 1 week | Usually 2–4 weeks |
| Cranial nerve risk | Lower, due to less dissection | Small but recognised (~5–8% transient) |
| Best suited for | High surgical risk patients; anatomically challenging cases | Standard and lower surgical risk patients; broadest evidence base |
The 2022 Society for Vascular Surgery guidelines recommend TCAR as a treatment option for patients with significant carotid stenosis who are at high risk for open surgery.
Why choose RIVEA for TCAR
RIVEA is a dedicated vascular and interventional radiology centre in Hyderabad and is equipped to offer the combination of carotid expertise, endovascular training, and advanced imaging infrastructure that TCAR requires.
Specialist carotid expertise: Led by Dr. Syed Mohammed Ali Ahmed, a vascular and endovascular surgeon with advanced training in carotid artery disease and complex vascular intervention.
Both open and endovascular options: We perform both TCAR and open surgical procedures. The recommendation you receive is based on what your anatomy and risk profile indicate.
Allia IGS 7 hybrid OR: TCAR is performed on the GE HealthCare Allia IGS 7, with robotic auto-positioning, real-time dose optimisation, and augmented reality vessel navigation.
FAQs
Am I a candidate for TCAR, or would open surgery be better for me?
That depends on the degree of narrowing in your artery, the location of the blockage, your age, and your other medical conditions. TCAR is generally preferred when open surgery carries elevated risk due to prior neck surgery, significant cardiac conditions, or challenging anatomy. For lower-risk patients, carotid endarterectomy has a longer evidence base and is often the better choice. We review your imaging and medical history before making any recommendation.
What are the key benefits of TCAR over surgery?
Transcarotid Artery Revascularisation (TCAR) is a minimally invasive treatment option for selected patients with carotid artery disease. It uses temporary blood flow reversal to help prevent plaque debris from reaching the brain during the procedure, potentially reducing the risk of procedural stroke. Compared with conventional carotid surgery, TCAR requires a smaller incision and may support a shorter recovery period. It can be particularly useful for patients in whom traditional carotid surgery carries increased risk, depending on their anatomy and overall health. Many patients return to routine activities within days, although recovery varies.
Will I be awake during the procedure?
TCAR can be done under local anaesthesia (awake but sedated, with no pain) or general anaesthesia. Under local anaesthesia, the surgical team can ask simple questions to monitor brain function as an added safety measure. The choice is made based on your surgeon’s assessment and your preference.
How long will I need to take blood thinners?
Dual antiplatelet therapy is prescribed after TCAR to prevent clot formation inside the stent. The course is usually at least one month, and often longer depending on your cardiovascular risk. Your surgeon will specify the regimen at discharge and review it at follow-up. Do not adjust or stop these medications without consulting us.
What follow-up is required?
A carotid duplex ultrasound is scheduled at 30 days to confirm the stent is open and functioning, and then annually. These appointments are important as a small percentage of patients develop in-stent restenosis over time, and early detection makes management straightforward. Stroke risk factors such as blood pressure, cholesterol, diabetes should also be actively managed with your doctor.
Does TCAR treat the underlying cause of the disease?
TCAR treats the blockage and reduces your immediate stroke risk. It does not address and indeed cannot treat the underlying atherosclerosis that caused plaque to accumulate. Controlling blood pressure, LDL cholesterol, blood sugar, and smoking remains essential after the procedure and is what determines long-term outcome.
How do I know if I’m eligible?
We use imaging tests (ultrasound, CT angiography) and health assessments to determine if TCAR is right for you.
What are the potential risks of TCAR?
Possible risks include:
- Stroke
- Heart attack
- Carotid artery or cranial nerve damage
- Bleeding or swelling at the incision site
You will be informed of these risks by your surgical team and they will take every precaution to ensure safety throughout the procedure and recovery.
Click here to learn more about:
Carotid Artery Disease (CAD)
For any inquiries, post your query here:
Ask Rivea
Contact us today to explore your options.
Call Now
Our Team

- International Journal of Stroke (2021). Stroke in India: A systematic review of the incidence, prevalence, and case fatality. doi:10.1177/17474930211027834.
- Annals of Vascular Surgery — Brief Reports and Innovations (2024). An evolution in carotid care: Contemporary TCAR data and optimization techniques. Nguyen T, Shames M, Bailey CJ.
- International Angiology (2025). The role of transcarotid artery revascularization in symptomatic carotid stenosis — review including 2022 SVS guideline recommendations. doi:10.23736/S0392-9590.25.05450-1.
- Stroke (April 2024). Transcarotid Arterial Revascularization of Symptomatic Internal Carotid Artery Disease: A Systematic Review and Study-Level Meta-Analysis.
- GE HealthCare. Allia IGS 7 for Interventional Image Guided Systems.
- GE HealthCare. Allia IGS 7 for Interventional Image Guided Systems.
- Cureus (2024). Mounting Stroke Crisis in India: A Systematic Review. PMC11052531.
- Society for Vascular Surgery Clinical Practice Guidelines for Management of Extracranial Cerebrovascular Disease